

Assistant Professor of CS at @JohnsHopkins, Part-time Visiting Scientist @AbridgeHQ. Previously: Postdoc at @CarnegieMellon. PhD from @MIT_CSAIL.
Baltimore, MD
Joined August 2011
- Tweets258
- Following1K
- Followers2.1K
- Likes5K




Looking for a postdoc in AI? Consider applying to the @HopkinsDSAI postdoctoral fellowship program at Johns Hopkins!
I mentor postdocs in this program, so feel free to mention my name as a potential mentor in your application :)
Apply by Dec. 11: apply.interfolio.com/196237

Join us in advancing data science and AI research! The Johns Hopkins Data Science and AI Institute Postdoctoral Fellowship Program is now accepting applications for the 2027–2028 academic year. Apply now! Deadline: Dec. 11, 2026.
Details and apply: apply.interfolio.com/196237
If you’re at CHIL in Seattle, check out our paper, led by @andrewzw20 !


Michael Oberst retweeted

1/ Excited to join Abridge to lead Engineering for AI Clinical Decision Support!
AI in healthcare is finally crossing the gap from “impressive demos” to real clinical impact.
Come join my group at Johns Hopkins!
I'm recruiting CS PhD students for Fall'26 (deadline: Dec 15) who are interested in safe/reliable AI in healthcare. See my website (link in reply) for more info.
I'm also headed to #NeurIPS, and happy to chat with prospective students!

For more information about me and my group, see my website, which also has information on applying to the CS PhD program (michaelkoberst.com/)

1
2
234
More broadly, JHU is an increasingly exciting place to do research in AI and ML, with huge investments in faculty, students, and compute. Just last year we hired 22 (!) new faculty in Data Science and AI! ai.jhu.edu/news/data-science…
4
1
179
Michael Oberst retweeted

LLMs tend to prioritize helpfulness > reason. We show that safety-aware, compute-efficient fine-tuning helps models reason more critically in healthcare domain, and generalizes to improved safety alignment across other domains.
nature.com/articles/s41746-0…

Michael Oberst retweeted

New #NeurIPS2025 paper: how should we evaluate machine learning models without a large, labeled dataset? We introduce Semi-Supervised Model Evaluation (SSME), which uses labeled and unlabeled data to estimate performance! We find SSME is far more accurate than standard methods.

Excited to welcome a lot of new colleagues!
#HopkinsDSAI welcomes 22 new faculty members, who join more than 150 DSAI faculty members across @JohnsHopkins in advancing the study of data science, machine learning, and #AI and translation to a range of critical and emerging fields.
ai.jhu.edu/news/data-science…

Michael Oberst retweeted

Excited to talk about our work on evaluating *medically adapted* LLMs and VLMs, covering additional results since our oral presentation at EMNLP 2024.
If you ever wondered whether Med-* LLMs/VLMs are really better than their general-domain counterparts, come check it out on 8/4!

This Monday, Daniel Jeong from Carnegie Mellon University will be joining us to talk about his work on the limited impact of medical adaptation of LLMs and VLMs. Catch it at 1-2pm PT this Monday on Zoom! Subscribe to mailman.stanford.edu/mailman… #ML #AI #medicine #healthcare

Michael Oberst retweeted

🧵 Academic job market season is almost here! There's so much rarely discussed—nutrition, mental and physical health, uncertainty, and more. I'm sharing my statements, essential blogs, and personal lessons here, with more to come in the upcoming weeks! ⬇️ (1/N)
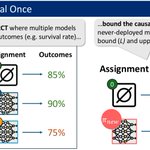
Randomized trials (RCTs) help evaluate if deploying AI/ML systems actually improves outcomes (e.g., increases survival rates in a healthcare context)
But AI/ML models can change: Do we need a new RCT every time we update the model? Not necessarily, as we show in our UAI paper!

ALT Abstract of paper titled "Just Trial Once: Ongoing Causal Validation of Machine Learning Models"
These findings are also relevant for the design of new trials!
For instance, deploying *multiple models* in a trial has two benefits: (1) it allows us to construct tighter bounds for new models, and (2) it allows us to test whether these assumptions hold in practice.
1
2
219
For more details, see the paper / poster!
And if you're at UAI, check out the talk and poster today! Jacob (not on social media) and I are around at UAI, so reach out if you're interested in chatting more!
Paper: arxiv.org/abs/2502.09467
Poster: michaelkoberst.com/assets/pa…
1
195
Michael Oberst retweeted

Excited to be here at #ICML2025 to present our paper on 'pragmatic misalignment' in (deployed!) RAG systems: narrowly "accurate" responses that can be profoundly misinterpreted by readers.
It's especially dangerous for consequential domains like medicine! arxiv.org/pdf/2502.14898
