

CMO Los Angeles General Medical Center, hospitalist, infectious diseases expert, researcher
Joined March 2016
- Tweets16.8K
- Following162
- Followers26.6K
- Likes25.6K





Pinned Tweet
Updated Shorter Is Better tables! @absteward found a 2 wk vs. 12 wk 2-stage PJI RCT. Also @rachelpbaden identified a duplication in the CAP trials, so there are now 14 RCTs for CAP, not 15. Updated refs at
bradspellberg.com/shorter-is…


Brad Spellberg retweeted

An 85-year-old has symptomatic, macrolide-susceptible, noncavitary pulmonary MAC.
What is the SINGLE most important factor in your decision to offer treatment versus observation?
#IDtwitter @BradSpellberg @DrToddLee @ABsteward @dralicehan @PaulSaxMD @DousaKhalid
13%Frailty/functional status
3%Estimated life expectancy
19%MAC severity/progression
65%Patient goals/preference
31 votes • 18 hoursI like numbers. This discussion done in detail in WikiGuidelines on IE. From 2 papers (Fowler '03 Arch Int Med; Ostergaard '22 OFID), pre-test prob of IE with S. aureus in blood is 1 in 8 (12.5%). Higher if community onset. Lower if line-associated. Higher if more bottles +.

I am not always 100 percent consistent. Community onset with no obvious source most of the time I'm treating 4 weeks...like @BradSpellberg said, if it's 1 bottle and neg TTE yeah...but I vary sometimes based on VBM (vibes based medicine)
and decide overall what your pre-echo prob is. -TTE if it's well visualized study has -LR of 0.3. Meaning, if youre pre-test prob is anything over 6%, your post prob is going to be >2%, and you need a TEE to exclude IE. Unless...
Brad Spellberg retweeted
@DrToddLee @BradSpellberg @syctong @PaulSaxMD @ASPphysician @dralicehan @Josh_S_Davis @IDPharmacometrx @IDstewardship @ABsteward @DrNeilStone @CarlosdelRio7 @IDSAInfo @ESCMID @CIDJournal @SIDPharm #IDTWITTER
15%A
50%B
8%C
27%D
60 votes • 9 hoursShout out to my friend Dr. Henry Anyimadu, for his new book about the AMR crisis, Beyond the Cure. I was honored to write the forward. His closing charge: Use antibiotics like a shared inheritance: only when needed, and always with care. Check it out!
amazon.com/dp/B0GR5S39WL/ref…

Brad Spellberg retweeted

I respect experts, but the scientific process even more. Evidence should outrank eminence. Barry Marshall was a junior doctor when he helped overturn ulcer dogma. Questions deserve answers on their merits. Trust grows when experts explain and engage with evidence.
Brad Spellberg retweeted

I'm going to go with"the data" I'm following the evidence based practice not the "eminent experts".

Brad Spellberg retweeted
The central issue is not whether cefiderocol works. It is whether the certainty implied by a recommendation is proportional to the quality of its supporting evidence. This is why I like so much Wikiguidelines because acknowled uncertainty in a humble way, not from an Ivory Tower

Brad Spellberg retweeted

Real cherry-picking citing a Chinese study but not the meta-analysis by Karakonstantis (quoted only for non-fermenters) finding high rate of Cef-non susceptibility among NDM-CRE (I can confirm it from an Italian viewpoint)
pubmed.ncbi.nlm.nih.gov/3766…

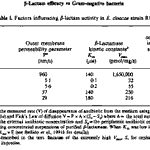
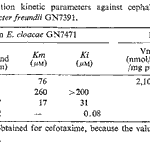
Special shout out to @laocarinadetapi, who has helped me understand this table, which may be key to understanding the entire controversy. He has explained to me that yes, Vmax higher for cefepime means that cefepime is absolutely hydrolyzed by AmpC, even faster than others. But..


The Vmax occurs at the Km (i.e., when the enzyme is saturated by the concentration of the substrate). The key here is that Cefepime's Km is 150 micromolar, but its concentration in the periplasm at the MIC concentration is only 250 NANOmolar (700-fold below the Km.
As such, cefepime is much less hydrolyzed than other cephalosporins because the Km is much higher than the actual periplasmic concentration. So there just isn't much substrate inside the enzyme to get hydrolyzed. Thank you @laocarinadetapi. for clarifying this confusing topic!
Brad Spellberg retweeted
💊 The susceptibility results are back.
After surgical debridement of G. bronchialis osteomyelitis, several agents appear active in vitro.
Assuming good source control and clinical stability, which would you favor for prolonged therapy? #IDTWITTER
23%Moxifloxacin
60%TMP-SMX
10%linezo/Tidezolid
7%Ceftriaxone
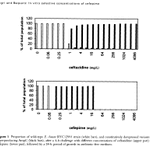
124 votes • Final resultsSo, check this out from the Negri paper. At concentrations of 0.125 mcg/ml cefepime you select for derepressed AmpC after only 4 hours of incubation. So it definitely isn't that good at preventing derepression.


