
AP/CP Pathologist @KingsCollegeLon Trained @MayoClinicPath @Yalepathology @NU_pathology | Digital Pathology | AI in Medicine | Sharing real diagnostic cases
Joined October 2025
- Tweets456
- Following7.4K
- Followers822
- Likes5.4K





Your first mistake in the lab is a map, not a verdict.
A blood bank tech posted online after being called into the QA office over a workup from the week before: an AB patient with an extra reaction on the reverse A cells. "I'm so embarrassed."
A miss in the lab usually passes several steps before anyone sees it: the bench, the review, the second check. Each of those steps is a place to fix.
My rule: replace blame with a process fix within 24 hours, and share the change.
#LabQualityImprovement #BloodBankSafety #LaboratoryLeadership
Can a pyogenic granuloma really grow on a vocal cord?
That was the whole question behind this second-opinion request.
A 35-year-old man with a progressive change in his voice. A lesion on the true vocal cord. The original diagnosis: pyogenic granuloma.
Under the microscope it was classic: lobules of thin-walled capillaries, edematous stroma, no dysplasia.
It is rare in that place, yet the vocal cord's constant vibration and rich small vessels make it fertile ground for this reactive lesion.
#RareMedicalCases #VoiceDisorders #DiagnosticPathology
The diagnosis was right. The location was what needed a second look.

What happens to a CK of 97,000 before anyone sees it:
• the analyzer flags it above its measuring range
• the sample is diluted, run again, and the result multiplied back
• if it is still too high, it is diluted again, up to a limit the lab director set
• beyond that limit, the report says "greater than," never a guessed number
One story shared online had exactly this: a CK of about 97,000 after a boxing camp, diluted three times before the lab could report it.
Every step takes time, and none of it is the lab being slow.
#BehindTheLabResults #CreatineKinase #LabMedicine
HIRSCHSPRUNG DISEASE: ONE WRONG BIOPSY. ONE WRONG DIAGNOSIS. A CHILD’S FUTURE AT STAKE.
Where to biopsy? How deep? Where are the ganglion cells?
5 critical pathology pearls:
Biopsy ≥2 cm above the dentate line.
Adequate SUBMUCOSA is essential.
Muscularis mucosae alone is NOT enough.
Muscularis propria is NOT routinely required.
H&E + calretinin; S100/SOX10 can highlight nerves.
The dilemma? Proving that ganglion cells are ABSENT.
In Hirschsprung disease, biopsy adequacy is patient safety.
#HirschsprungDisease #Pathology



AI is only as clinically intelligent as the data we feed it.
When a consumer AI health tool was tested on 960 cases, it sent 52% of true emergencies to a check within 24 to 48 hours instead of the emergency department.
Among them was diabetic ketoacidosis, a condition defined by glucose, ketones and blood acidity.
Those are numbers a typed description of symptoms does not contain.
#AIInHealthcare #PatientSafety #LaboratoryMedicine
In 1,000 women co-tested in our lab, 72% of the HPV genotype-positive cases carried only non-16/18 high-risk types.
Only 28% had HPV 16 or 18.
Yet most screening and vaccine conversations start, and often end, with 16 and 18.
Local data should shape who we screen and how we explain the result.
#HPVAwareness #CervicalCancerScreening #LaboratoryMedicine
Everyone checks the diagnosis. Few check whose tissue it is.
One study did what most labs never do: it tested almost 13,000 prostate biopsies to confirm the tissue belonged to the patient on the label.
0.26% were complete switches between patients.
Another 0.67% contained tissue from a second patient.
None had been suspected beforehand.
A correct reading of the wrong patient's tissue is still a wrong diagnosis.
#RightDiagnosisWrongPatient #PatientSafety #SpecimenIdentification #Pathology
What if AUTOIMMUNITY is not simply the immune system attacking SELF… but the immune system losing its ability to TRUST?
We have spent decades teaching autoimmunity as “SELF vs NON-SELF.”
But that’s only ONE face of a much bigger story.
Autoimmunity has MANY faces:
🧬 Sometimes the immune system LEARNS the wrong lesson.
🧠 Sometimes it FORGETS what it once tolerated.
🔬 Sometimes it DISCOVERS antigens it was never exposed to before.
Different mechanisms. Different triggers. Different patients.
But one concept connects them all:
IMMUNE TOLERANCE.
In our culture, we have a beautiful concept:
حُسن الظن (Husn Al-Dhann)
Giving others the benefit of the doubt. Not assuming everyone is an enemy.
A healthy immune system does something remarkably similar.
Every second, it encounters thousands of signals.
And its greatest achievement isn’t always deciding what to ATTACK.
It’s knowing what to LEAVE ALONE.
Regulatory T cells (Tregs) help maintain that delicate balance.
Because not every antigen is a threat.
Not every immune response is protective.
And not every battle needs to be fought.
When tolerance breaks, autoimmunity can emerge.
Perhaps the most important question in autoimmunity isn’t WHY the immune system attacks…
It’s WHY it stopped tolerating.
And perhaps the greatest intelligence of our immune system is not its ability to fight, but its wisdom to know when NOT to fight.
#Autoimmunity #Immunology #ImmuneTolerance



What a real sign-off is built on:
• good care broken into observable behaviors
• training on those behaviors
• an audit of real encounters
• the same measures, checked again
When our phlebotomy patient-experience scores dropped, that is what we did: 100 real encounters, 41 measures.
Professional self-introduction went from 20% to 75%.
Time on the bench is not competence.
#TimeIsNotCompetence #BeyondTheBench #CompetencyMatters #Phlebotomy
A patient's blood type changed. The lab was right.
After a bone marrow transplant from a donor with a different blood group, the patient's red cells gradually switch to the donor's type.
For a while, typing shows both.
That is the donor marrow taking over, not an error.
A blood bank tech shared exactly this online, and colleagues replied that it was a good sign: the graft was doing its job.
Until it settles, every transfusion has to suit both blood types.
#BloodTypeChanged #NotALabError #BoneMarrowTransplant #StemCellTransplant
The analyzer found a hemoglobin variant while running an A1C.
Should the report say so?
Some A1C methods separate hemoglobins and flag variants nobody asked about.
Some variants can also make certain A1C methods read wrong.
Labs handle it differently: a report comment, a call to the clinician, or a referral for confirmation.
Lab colleagues: what does your lab do?
#BeyondTheA1C #UnexpectedLabFindings #HemoglobinVariants
We’ve been teaching autoimmunity as “SELF vs NON-SELF.”
But what if that’s only one face of the disease?
Autoimmunity is far more complex.
The immune system doesn’t just attack the wrong target. Sometimes, it:
🧬 LEARNS the wrong lesson.
🧠 FORGETS what it once tolerated.
🔬 DISCOVERS antigens it was never meant to encounter.
Three different paths. One outcome: loss of immune tolerance.
And here’s the fascinating part:
The same trigger can cause devastating disease in one person and absolutely nothing in another.
That’s why autoimmunity isn’t simply about recognizing SELF.
It’s about learning, memory, exposure, and above all, TOLERANCE.
Maybe the biggest question in autoimmunity isn’t WHY the immune system attacks.
It’s WHY it stopped tolerating.
#Autoimmunity #Immunology #ImmuneTolerance


Which tells you more: a result outside the range, or a result far from the patient's own last one?
A reference range compares you with a population.
A delta check compares you with yourself.
A creatinine inside the range can still be a big jump for that patient.
A hemoglobin steady all week that suddenly jumps today raises the real question: is the patient sicker, or is this someone else's blood?
Often the best reference is the patient's own history.

Same block, two HER2 FISH results.
The case came to us as HER2 IHC 2+, equivocal.
FISH done elsewhere was reported negative.
We reviewed the morphology, repeated the IHC, repeated the FISH.
It was a Group 3 result, so we did the required blinded second count.
Integrated interpretation: HER2 positive.
That opens the door to HER2-targeted therapy.
One result is never the whole answer.
#HER2 #HER2Positive #BreastCancer #BreastCancerAwareness #PrecisionOncology

Same disease. Two start ages.
In 2024, the US Preventive Services Task Force said mammograms every two years from 40.
This year, the American College of Physicians kept routine screening at 50 and made the 40s a shared decision.
One radiologist's reply online: starting at 50 "is going to get people killed."
In Saudi Arabia, the median age at breast cancer diagnosis was 46 to 52 over two decades.
Part of that reflects a younger population, so it calls for local age-specific rates, not a verdict.
Whose numbers should set the rule here?
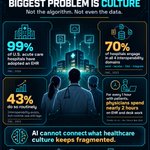
Healthcare AI’s biggest obstacle isn’t the algorithm. It isn’t even the data. It’s the CULTURE—and our limited understanding of our own systems.
We have incredibly sophisticated infrastructure, powerful middleware, advanced LIS, and enormous amounts of clinical data.
Yet how much of their hidden potential do we actually understand?
We depend almost entirely on IT teams, who are already overstretched and may not fully understand the complexities of clinical decision-making.
Physicians understand the medicine. IT understands the technology.
But who understands what happens BETWEEN them?
That is where fragmentation begins. And where interoperability often fails.
Physicians and laboratory professionals must become active architects of digital healthcare, not just users of technology.
Without clinical ownership, digital literacy, and connected workflows, forget about scaling AI!
We need the ecosystem BEFORE the algorithm.
This is why I’m writing LAB BLACK BOXES.
A journey inside the hidden intelligence of our laboratory systems.
Real cases. Real errors. Real interfaces. Real frustrations. And practical solutions.
Because sometimes, the greatest innovation doesn’t require purchasing another system.
It requires understanding the one you already own.
#HealthcareAI #DigitalHealth #LaboratoryMedicine


