





AM23 retweeted

Only 2-4 months until the wider market starts to perceive that #AVCT's AVA6103 could genuinely become a $20bn, $30bn, >$40bn per annum drug.
The best selling oncology drug in history.
That is, until the data for AVA6207 begin to emerge...!
AM23 retweeted

#AVCT
Cohort 1
Began end of March
On 10 September, two patients remained on drug. That’s 5.5 months of disease stabilisation across stage 4 pancreatic cancer patients. Achieved with a 1.5mg dose of AVA6103.
I.e. their tumours are not seeing progression.
Cohort 2
Began ~mid May
On 10 September, five patients remained on drug. That’s ~4 months of disease stabilisation across stage 4 pancreatic/CRC/cervical cancer patients. Achieved with a 3mg dose of AVA6103.
I.e. their tumours are not seeing progression
Cohort 3
Began ~early July
On 10 September, (all) seven patients remained on drug. That’s ~2.5 months of disease stabilisation across stage 4 pancreatic/CRC/breast patients. Achieved with a 4.5mg dose of AVA6103
I.e. their tumours are not seeing progression
Cohort 4
Began began ~mid August
Dosing 6.8mg. Just below the Enhertu equivalent. Cohort 4 has completed enrolment as of 23 October.
Enrollment is ongoing in both arms of the study. 8 months into trial end of November.
It is quite clear AVA6103 is working. In human.
Funded well into May 2027. That’s ~7 months of funding after a 68p fundraise which saw the directors take £660k.
Cohort 5 (current cohort) projected to match the absolute dose of Enhertu.
Q2W scanned every 8 weeks.
Q3W scanned every 6 weeks.
Couple of biopsies up their sleeves. They know exactly what this drug is doing 7.5 months into trial.
The amount of ‘ hot takes’ I’ve read which are concerned about “funding into May when AVA6103 efficacy is not due to H1 2027” demonstrates enormous naivety.
For two reasons:
(1) the trial is flying, you’ll see efficacy early H1 2027 at this rate;
(2) the efficacy data (as a package) for AVA6103 is actually irrelevant for the assets AVCT is seeking to deal on: a 3rd party warhead; AVA6000; AVA6207.
Yes, the AVA6103 data supports the negotiations but they are not dealing on AVA6103.
Proving AVA6103 is working (to the extent the tech can transfer to a third party warhead) was done when they RNS’ed preCISION was proven.
Partners will receive this data under NDA on a constant basis.
Far more important are the commercials of those deals, which improve as the AVA6103 data grows.
That is to say the 6103 data *supports* the value discussion, rather than being the arbiter of any deal(s).
Crazy thought I know, but they have a strategy.
X3 separate deal avenues to deal on before May 2027.
Lots of noise. Little logic.


#AVCT Advance further into pioneering oncology.....
A dual payload to be presented at EORTC in 2 weeks time. This is highly significant. A very high chance the second payload is pharma owned = Deal time.
There are only 3 dual payload ADC drugs in the clinic globally. Zero Dual PDCs which Avacta specialise in. First mover advantage in dual payload PDC's another first.
They really are at the tip of the spear here adding an ATRI inhibitor to inhibit resistance mechanisms. Pair that with Exatecan used in the AVA6103 trial and you you have a lethal cocktail pharma can only dream of before Avacta's arrival.
avacta.com/avacta-to-present…
1/2
2/2
So in just a few short years Avacta have....
1. Removed cardio toxicity from Doxorubicin - A 50 year problem pharma failed to address.
2. The FDA removed the lifetime limit of AVA6000 which uses Doxorubicin as the warhead. This was the first time ever in a P1A trial a lifetime limit had been removed!
3. Then taken the most potent drug in its class Exatecan again one pharma could not harness at full strength and completely changed its safety and tolerability profile, its therapeutic index and half life.
4. Now takes Exatecan and pairs it with an ATRI inhibitor!!
The key differentiator here is 'Precision' the Avacta tumour targeting and delivery mechanism which just so happens to works on 90% of all solid tumours!!!!They have cracked the safety and tolerability limitations which is still a prolific problem for pharma. This enables them to target the tumour more successfully, deliver the payload to the tumour and see a significant reduction in typical toxicities.
Precision is checkmate for so much of the current industry thinking. Well done the AVCT a team of 20-25 people has done all that!!
AM23 retweeted

Market is acting like #AVCT is funded into December 2026, rather than May 2027.
A lot can happen in a very short time in biotech.
And Avacta has x5 shots on goal:
AVA6000 (SGC)
AVA6000 (TNBC)
AVA6103 (multiple shots)
AVA6207 (also multiple shots)
PRECISION (to a 3rd party warhead)
Never been more confident - today buying Avacta is the cheapest and safest that it has ever been.
So I did !

Over to #AVCT…..pretty sure they will have something to say here….!!!
A very well timed article. They don’t like talking about the constraints of Enhertu but Avacta does with confidence regularly now. They know!!!
“To design a molecule stronger than Enhertu in HER2-positive breast cancer, I think maybe we can design it on paper, but to clinically prove it is stronger is just too difficult,” he said.
fiercebiotech.com/biotech/ad…

AM23 retweeted
#AVCT’s AVA6103 works.
“Mechanistically, the sustained release mechanism is playing out as we expect.”
“Findings increase confidence that the nonclinical-to-clinical translation is performing as intended - exactly as we anticipated.”

Watch episode 16 of our R&D Spotlight series, where Avacta Chief Executive Officer @coughlin582 takes a deep dive into the AVA6103 data presented at ESMO 2026. avacta.wistia.com/s/xs4ra3k8… #AVCT

AM23 retweeted
#AVCT
Novartis bought FAP2286 from Clovis in bankruptcy.
$50m upfront; $333.75m in regulatory milestones (split equally between P1b; P2; P3); $297m in future sales payments.
FAP2286 had dosed 11 patients at the time of sale.
Efficacy: 1 patient of the 11 treated in Phase 1 saw a partial response.
Safety: 45.5% of patients saw Grade 3/4 adverse events.
You'll struggle to find a better representation of how cheap AVCT (£311m) is today than this sale. Achieved in bankruptcy.
X2 drugs in clinic, north of 150 patients dosed across those programmes. A clear USP. Going after ADCs. Safety impeccable. No loss of activation enzyme on tumour destruction.
AVCT could down all tools tomorrow, put the entire Co up for auction and sell for multiples of today’s SP.
Funny old market.
I’m a buyer here. AVA6103 is currently reading out critical C3 data (and every oncologist linked to the trial is promoting their collaboration…).
Another outstanding update from #AVCT this morning.
AVA6000 has been quietly ticking off it's list of achievements.
1. Standard Doxorubicin has a lifetime limit precisely because of cardio toxicity. The impact is a limit on treatment cycles 4-6 dependent on dose.
The answer is Avacta's AVA6000 = Zero cardio toxicity, many more cycles 12 referenced in the RNS today = more time with your family and reduced toxicity.
2. AVA6000 is the first drug EVER to have the lifetime limit removed by the FDA in a phase 1 trial. Think about that.
3. AVA6000 PFS for SGC nearly doubled and may well improve further.
4. TNBC efficacy seen!! (see poster) Many forget Doxorubicin is used in combo trials as part of keynote 522 along side a $30bn revenue drug Keytruda which comes off patent in 2028...Merck have a massive patent cliff approaching. It is used as Dox is effective!
5. As the first ever Precision drug it has proven the IP works in the clinic. AVA6103 further enhances the wider platform capability. The FDA endorsements will keep coming as the story unfolds imo. Rinse and repeat.
Many forget the positives of AVA6000 because the trial was a victim of it's own success...could not find an MTD, a 5yr phase 1 trial and not yet partnered but it has set a new standard that only demonstrates further there is a huge void to fill which will improve patient care with Precision drugs.
At some point soon we will be playing a game of 'Knock Knock'....'Who's there?'
AM23 retweeted
#AVCT
AVA6000 contains a peptide. That peptide masks doxorubicin to the extent an 80 year old suffering from triple negative breast cancer is able to safely receive preCISION-doxorubicin. And work.
The risks of chemotherapy induced toxicity due to reduced organ reserve, comorbidities and general frailty for an 80 year old are clear.
Yet it’s working. Quite clearly.
Why is it working?
It has an exceptional safety profile. Due to this peptide’s exceptional specificity.
Now consider the same peptide is in AVA6103.
AVA6103 has an additional modified capping group and a linker (which are designed to sustain the release of Exatecan for days, rather than hours).
We know from the human PK to date, that is exactly what AVA6103 is doing (with exceptional alignment between pre-clinical and clinical data).
It’s extending release of Exatecan because the capping group and linker are working. In human.
It’s safe because the peptide (employed in both AVA6000 and AVA6103) is so specific.
We have seen the clean safety profile through cohorts 1-3 of AVA6103. Thanks to the peptide.
We have seen the FDA remove the dosing limit (for the first time in the history of a P1 drug) in AVA6000. Thanks to the peptide.
We are now seeing just how safe this peptide makes toxic drugs. 5 & 1/4 years of combined data back this up across Top1 and Top2 inhibitors.
Tomorrow AVA6103 will be 30 weeks into clinic.
Tomorrow AVCT will outline how AVA6000 is demolishing the benchmark in Salivary Gland Cancer.
A prolonged median PFS of 11.4 months.
That is nearly doubling the benchmark in the first and second line setting (both chemotherapy and targeted therapy).
AVA6000 in SGC deals on this PFS. Quite clearly.
In addition to all this, I can’t help but wonder whether AVA6000 in TNBC is going to also find a partnership with generic Keytruda in the future.
Patent expiry in 2028? $30+Bn pa drug. Often used in tandem with doxorubicin which has now been made safe by preCISION.
Keynote 522(P)? The trial Coughlin said she would most like to run for 6000.
AVA6207 on the cusp of revealing its warheads.
AVA6103 biopsies incoming.
AVA6000 demolishing the PFS in SGC.
Looking forward to hearing more about FAP recruitment, durability and the real world impact of AVA6000 when the company explains the findings to the market tomorrow.
‘Bloody science project’.


AM23 retweeted

We are delighted to present 2 data sets at #ESMO26 - #AVCT Trials in Progress with AVA6103 shows some critical platform data showing mechanistic evidence for fibroblast recruitment, rapid and deep tumor penetration and enhanced payload exposure over traditional ADC
#LetsDoThis
At #ESMO26, we’re presenting the FOCUS-01 trial design and new preclinical data for AVA6103 (FAP-Exd), our first Next Gen pre|CISION® PDC, including activity in Enhertu®-resistant tumor models.
avacta.com/avacta-highlights… #preCISION #NextGenLoading #AVCT

AM23 retweeted
Most important sentence in an #AVCT RNS for a long while.
We’re home. Nearly dry.
🚀


AM23 retweeted

I'm increasingly excited about Avacta #AVCT because I genuinely believe the next eight to twelve weeks could be transformational. As everyone knows, they've developed a technology that allows incredibly powerful drugs to be delivered much more precisely to 1/23
Another outstanding performance from Chris on Thursday. #AVCT
When you know you know and she definitely KNOWS!
1. FDA approved the removal of the life time allowance on a 50yr old chemo drug Doxorubicin in a Phase 1A safety trial last year. AVA6000 was the first drug ever to have achieved this in P1A…..
2. You then harness Exatecan aka ‘The Beast’ the most potent drug in its class where pharma failed to tame its toxicity for years. AVA6103 is that Precision drug now in clinical trials.
3. You state you can put almost any warhead on precision the delivery mechanism and have hundreds of options in the locker.
4. You compare your safety profile to a $5bn per year blockbuster drug Enhertu only months into your AVA6103 trial and blitz it!
5. You don’t sign up a dozen premier US trial sites if AVA6103 wasn’t working!
Chris Coughlin @coughlin582 will be remembered as leading a small team of incredible talents who redefined what was possible and made it happen.
Imagine you get diagnosed with this awful disease but there are new treatment options where the historical fear of awful side effects is no longer a fear as the standard of care is a Precision drug, where you can safely have more doses or higher doses giving you the best chance of survival at the same time.
I believe the next few months will establish Avacta as the most disruptive company most have never heard of on the ADC/ oncology landscape.
Most forget P1A patients are typically end of life who are prepared to aid science by their selfless acts to ensure others have a tomorrow. What Heroes! Thank you.
AM23 retweeted
TVR5 fully supports the #AVCT board’s strategy to protect the inherent value of the pipeline, given the strength of the AVA6103 data to date. We expect the board to close its first validating deal in Q4 2026, following this bolstering of the company’s negotiating position.
You don't just add 7 new trial sites at some of the most prestigious oncology centers globally unless your trial is going well. Huge cost for this but even bigger validation = Green lights.
Gastric in focus and recalling CC comments from a previous event a year ago where she stated Gastric was her first indication pick at the time to see responses!
Very telling they have been telling us a lot about the progress with PDAC the likely hardest of the 6 indications to treat first....Have they cracked them all?
Well done AVCT #AVCT
mskcc.org/cancer-care/clinic…

AM23 retweeted
#AVCT
Enhertu Phase 1a was very good at disease control, even at the lowest doses.
21/23 saw stable disease.
There were 10/23 partial responses.
All of these partial responses, bar x1 patient, came at a dose of 5.4mg and above.
The single responder below this dose threshold was at 3.2mg.
There was 1/23 complete response.
There were just 2 cases of disease progressing. x1 at 3.2mg and the other dose not disclosed.
If AVA6103 is not controlling disease at the 6 month marker, it is not going head-to-head with Enhertu.
Yet there is not a single mention of “stable disease” or “disease control” in either of the recent RNS (post proving of the platform).
Instead, AVCT simply says it expects efficacy to follow, it expects a tumour reservoir, it expects the preclinical results to translate to clinic.
There is little chance the company speculates on these expectations, without having seen AVA6103 enabling disease stabilisation at these low dosing levels to date. Because that is exactly the Enhertu benchmark they are directly comparing against.
At the RP2D (5.4mg) the median time to response (TTR) for Enhertu is just 1.6 months.
I.e. The middle point in time when half of the patients who eventually responded to Enhertu first showed a clear improvement (tumour shrinkage that qualified as a partial response) on their scans. I.e. it works very quickly at the big doses and is likely to show at the time of the first scan (6 week marker).
DL4 should be right up there with Enhertu’s median TTR. If not better.
The DL3 cumulative exposure is now punchy. 7/7 remain on drug as of the last update.
To top it off AVCT is talking AVA6103 at a pancreatic cancer conference (an indication which Enhertu simply did not work, no matter how high the dose or the HER2 amplification).
A good reminder just how hard pancreatic is to crack.
So, what does matching or bettering Enhertu’s phase 1 data actually mean at this stage?
Easier to look at what the clinicians were saying about Enhertu’s (complete) Phase 1 data set. Copied below.
What followed for Daiichi?
Fast Track was granted based on the reported 22 patients treated at the time (20 evaluable).
Avacta is moving at twice the speed Daiichi was at this stage…


Zero concerns here. Excellent news out today. #AVCT
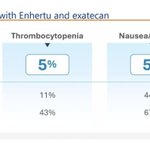
Only 9 days ago Avacta confirmed that AVA6103 is revolutionising how the most potent topo1 a drug pharma failed to harness in its naked form 'exatecan' is successfully delivered by precision.
To spell it out Precision is delivering Exatecan as the warhead in AVA6103, Enhertu uses a watered down version of exatecan and is a blockbuster drug ($5bn revenues this year) BUT yet your eyes doth not deceive you!
If you had a choice (sadly many don't in oncology) which one of the 3 outcomes would you pick? The significance of these differences cannot be highlighted enough as their impact on patient care, dosing and outcomes is vastly different.
1/2

Avcata are off to AACR this weekend to talk about pancreatic cancer one of 6 indications in the AVA6103 trial. You don't choose to crow about the hardest indication to treat unless you have supreme confidence and/or proof of efficacy imo already.
The table above only confirms part of the story, safety and tolerability. Enhertu is used today as it is effective so why wouldn't AVA6103 also lead to efficacy when it uses the full power of the warhead used in Enhertu? 2+2=4
Avacta blitzed the preclinical with 20/22 responses. Today they reiterate their confidence in the translation of that into the clinic. The market is asleep on this, they are stuck on Enhertu and Exatecan when AVA6103 has just surpassed them...by how much is the question I'm looking for answers on.
2/2
