

Urology Specialist Registrar in London, UK | Uro-Oncology & Academics | Tennis NUT 🎾 | Former @BJUIjournal Section Editor @BURSTurology VC |
London, England
Joined January 2012
- Tweets11.9K
- Following2.3K
- Followers1.3K
- Likes15.5K
Meg Kulkarni 💙 retweeted

We have recoded BAUS on Demand to improve functionality. Previous conference videos for @BAUSurology members. The views and likes counters are now working. A lot more content coming soon. Check it out:
baus.org.uk/mybaus/education…

Meg Kulkarni 💙 retweeted

A terrible loss. She was the world's premiere infectious disease reporter -- an icon for all of us in public health science and journalism alike.

It is hard to believe that Helen Branswell has passed away. Just heartbreaking.
On January 4, 2020, Helen wrote STAT's first story on a mystery pneumonia outbreak in China. She saw the pandemic coming well before anyone was paying attention.
Helen was a journalist who knew more than most of the experts she interviewed. She understood the science, the history and the politics of every outbreak she covered. She asked the hardest (and best) questions and never let me get away with a vague answer
Experts learned from her. I certainly did
It's hard to imagine a world of pandemics, biological threats and so much more without a Helen Branswell to explain it all.
statnews.com/2026/10/13/hele…
Meg Kulkarni 💙 retweeted

Dehiscence, infection, seroma, haematoma (DISH): development and validation of a new classification of surgical site outcomes
➡️ doi.org/10.1093/bjs/znag112
The proposed cross-specialty, global DISH Classification facilitates more comprehensive surveillance and audit of SSOs in clinical practice and research, by standardizing reporting of all relevant grades of clinical presentation and management of SSOs
Work by Giles Bond-Smith , Marja A Boermeester , David J Leaper , Philip L Russo , Antonia F Chen , the SSO Working Group Authors , the SSO Expert Panel , the SSO Validation Study Panel
#SoMe4Surgery #MedTwitter #SurgEd #Surgery @RCPSGTrainees @aecirujanos @SEIQuirurgica @iss_sic #MedicalTechniques @BJSAcademy @young_bjs @BJSOpen @evanscolorectal @robhinchliffe1 @bplwijn @MalinASund @nfmkok @TejedorPat @paulo_sutt @PVaughanShaw @JJEarnshaw @juliomayol @ksoreide #some4hpb #some4tpl @DPCG_official @pancreatitis_nl @PancreasClub #PancreasClub2023 #PancreaticCancer #Pancreatitis #HCC @PanCAN #PanCANawareness @EurPancClub @P_C_E_ @dice_europe #PancreaticCancer #cholangiocarcinoma #HPBSurgery #GallbladderCancer #Oncology #LiverSurgery #colorectalsurgery #StepUp4CRC @FightCRC @ACPGBI #ERAS @dice_europe #Crohn #proctology @Dukes_Club @ACPGBI_EduTrain @AECP_FAECP @PelvExGroup @escp_tweets @YouESCP #TeachMeColoproctology
#Some4COLoprocto #some4UGI #uppergi #esophagealcancer #gastriccancer #reflux @ISDE_net @Augishealth @roux_group @T4UGIS @SARONG_Trial @YoungIFSO #bariatricsurgery

Meg Kulkarni 💙 retweeted

I have noticed an up tick in PA anons and PA supporting accounts coming to give an opinion-on my feed- about my views on @lengreview PA protocols.
To help you, I have 3 things to say.
1. I don't have any influence in the system, I am not part of Council @RCPhysicians (powers that be terminated my time).
I have no voice that anyone takes much note of- especially in @NHSE_WTE @NHSEngland circles.
There's a reason I am not in the @HSJnews Non-white influential people list- it's because I don't have influence. That is a fact.
So don't worry at all about my view.
2. Making references to my recent loss in a derogatory way is more a reflection of your upbringing or lack of it.
I spend enough time nowadays in darkness- you can't make it worse.
Avoid it- you never know what happens in your own life in the future
3. You should have the same approach as I do to pro-PA views. I literally don't care at this point. I believe the way in which many have tried and are trying to use PAs is dangerous to the public. You don't agree.
Fine- it's a democracy.
But I will say what I believe to be true.
Also- if you bring heat to a conversation?
Don't flounce off when you get smoked in return.
Refer to point 3- I don't care about your opinion at this point
I hope that helps
Thanks and much love
Partha
Meg Kulkarni 💙 retweeted

Lymphocele cited as major reason in guidelines to avoid LND in prostate cancer. Here we show most almost all lymphoceles (42/43) come from Cloquet's node, which should not be removed during LND. auajournals.org/doi/10.1097/…
A really important topic and a brilliant interview.


Meg Kulkarni 💙 retweeted

Devastating news 💔
Rest in peace dear Rachna.
medicine.arizona.edu/news/20…
Meg Kulkarni 💙 retweeted

Any tips at #SMSNA26 for a replacement suture for those doing EDVs? I can’t get hold of Corza 10-0 double ended sutures that are 2.5cm length..only 30cm which is awful! Help! @donwglee can you ask @DrLipshultzTips @ScottLundyMDPhD @raevti @SaveYourSexLife @rbarbosa91 @dr_wardsam


Epididymovasostomy…. An excellent option for obstructive azoospermia in the right hands. Difficult to say, harder to spell and takes many years to perfect the surgery. Looking forward to sharing my video, discussing patients and tips/tricks for surgery at #WMSM2026 Friday 27th
This is excellent!!
Medicine is a humanity before it’s a science - never forget that!
❤️@GuysUrology

Due to do a RARP. Vulnerable Patient hasn’t showed up despite multiple calls and hospital transport failed to pick him up. Theatre team ready. Everything unwrapped. Solution? I got him an Uber. Met him at the door. Case done. @GuysUrology @GSTTnhs #darequamaccipere

Meg Kulkarni 💙 retweeted

If you're trying to build support for ergonomics at your institution, start somewhere practical:
• Reframe the problem
• Bring local data
• Find partners
• Start with one specific problem
• Don't stop at education
@https://surgicalergonomics.com/podcast/
🤖 Made with AI

Meg Kulkarni 💙 retweeted

🔬 PROTEUS y cáncer de próstata de alto riesgo: ¿estamos comparando las mismas poblaciones?
El ensayo PROTEUS ha abierto una nueva etapa en el tratamiento del cáncer de próstata de alto riesgo, demostrando beneficios de añadir apalutamida a la terapia de deprivación androgénica en el contexto perioperatorio.
Sin embargo, surge una pregunta fundamental: ¿representan las cohortes retrospectivas de pacientes elegibles para PROTEUS a la población realmente incluida en el ensayo?
📊 En nuestra carta destacamos tres aspectos:
🔹 Las diferencias entre los criterios de inclusión de un ensayo y las clasificaciones de riesgo de las guías EAU/NCCN pueden modificar significativamente la categorización de los pacientes.
🔹 La población incluida en PROTEUS presentaba características clínicas y patológicas más desfavorables que las observadas en algunas cohortes retrospectivas reconstruidas.
🔹 La intensificación terapéutica debe acompañarse de una selección adecuada de pacientes, evitando extrapolaciones que puedan conducir al sobretratamiento.
🎯 Ser elegible para un ensayo no significa necesariamente representar a la población finalmente incluida.
En una era de creciente intensificación terapéutica, interpretar correctamente la evidencia es tan importante como generar nuevos datos.
🔗 sciencedirect.com/science/ar…
@Lara__Rodriguez @GGiannarini @foxal72
#ProstateCancer
Meg Kulkarni 💙 retweeted
Comments on the protocol for PAs:
Regards the people who have done this.
It's no different to what I saw when RCP was making their interim document of scope.
A few of us stopped it from a complete slide at that point- and this panel doesn't have a dissenting voice- so it's mostly an echo chamber IMO.
FWIW?
I respect Gill Leng- and she has been-IMO- bench pressed by a skewed group.
It is why she is asking for as many people as possible to comment on this.
If we-as doctors- we want to support her and @lengreview recommendations, we support her through organisations as best as we can.
First the good news:
1. With the @TheBMA having put the PA protocol document in the public domain?
The @RCPhysicians is saved the hassle of mulling over whether to open it up formally.
Now that it's open, let Members & Fellows decide whether they want to take this level of supervisory responsibility.
Let the wider democracy give their views
2. It's a national scope work- so we are finally moving away from the nonsense of 'local scope'
Now the rest:
1. My personal view?
It's a flat No from secondary care perspective
No one has that level of supervisory capacity as stated in document due to job plan constraints.
And we have the 'Medical Education & Training Review' yet to land @DacreJane
Which means- we will have lesser trained people seeing undifferentiated patients- and cause harm.
2. In my opinion, it should be rejected by RCP et al- but I don't speak for all.
Write to your College.
If you- as a Resident Doctor- or Senior- feel this is ok?
Write too.
That is my view- and I will not want any of my loved ones to be seen by a PA as per this protocol.
I have the privilege to avoid that.
Question is- do you.
This document goes nowhere without support of @TheBMA @RCPhysicians @rcgp et al
I can guarantee you that @DHSCgovuk will not take on a pitched battle if all doctor organisations- the ones being asked to be the liability sponge- says 'No'
Over to all of you.
I know it feels tiring sometimes- battling the machine- while trying to improve patient safety
Yet- You only lose when you give up.
@mmamas1973 @djnicholl @Mumtaz_Patel_1 @OGMustafa @VictoriaTzB @SwordsFrankie


The questions must be asked
Less obfuscation, more transparency
Formal ask in place
Over to you @RCPhysicians
As a Fellow, we should be able to comment on the protocols as suggested by @lengreview
The 'era of transparency' should mean exactly that
@djnicholl @mmamas1973

Meg Kulkarni 💙 retweeted

Join the RSM Urology Section for a meeting exploring trauma, emergency urology and the evolving landscape of urgent urological care.
Find out more: rsm.ac.uk/events/urology/202…
Friday 16 October 2026 📅
9:00am to 5:00 pm BST⏲️
RSM, London📍

Meg Kulkarni 💙 retweeted
“Bridging the PSMA PET/CT access gap in prostate cancer: evidence, barriers, and priorities for implementation” addresses an increasingly challenge: strong evidence and guideline recommendations do not necessarily translate into timely and equitable access for patients.
🎯PSMA PET/CT has transformed prostate cancer imaging. However, access remains heterogeneous across countries, regions and institutions, with barriers including reimbursement, nuclear medicine capacity, radiopharmaceutical logistics, waiting times and variable referral pathways.
🇪🇺 Exploratory European data suggest that real-world use remains below the estimated eligible population, highlighting an implementation gap between evidence, recommendations and clinical practice.
🎯 Priorities for implementation include guideline-based eligibility, harmonised reimbursement, regional referral networks, adequate imaging and reporting capacity, multidisciplinary collaboration, and measurable access indicators.
The next challenge for PSMA PET/CT is not proving its value, but ensuring that eligible patients can access the right imaging at the right time, regardless of geography or institution.
#ProstateCancer #PSMAPET #Urology
link.springer.com/article/10…
@MRoupret @wjurol @InfoAeu @UrologiaClinico

Meg Kulkarni 💙 retweeted

The basic training of a doctor reduced to a poster due to the proliferation of non medically trained people seeing undifferentiated patients - if u have to use this poster, you are not trained medically and you should not be seeing patients @NHS

Meg Kulkarni 💙 retweeted

As part of @Uroweb #urologyweek and @TUF_tweets #urologyawarenessmonth we are hosting a kidney cancer awareness event @RoyalFreeNHS this Friday!
Drop in to @MaggiesRFH to learn about #kidneycancer, support available and meet our excellent multidisciplinary team!

Meg Kulkarni 💙 retweeted

Great point-counterpoint at the podium today: @veerukasi arguing biparametric MRI should be the new standard of care for prostate cancer diagnosis vs @RaisBahrami making the case to keep contrast. PRIME (JAMA 2025) says bpMRI is noninferior to mpMRI for csPCa (29.0% vs 29.6%, 555 men, 22 centers). Shorter scan, no gadolinium. The counterargument: DCE still helps with equivocal PI-RADS 3 lesions and better defines lesion size, which matters for focal therapy planning. Where do you land? @FocalSociety @Endo_Society #ProstateCancer #bpMRI #PRIMEtrial #FTS2026 @JAMA_current


Meg Kulkarni 💙 retweeted

When radical nephroureterectomy means dialysis, can we safely preserve the only kidney?
Our latest multicentre study in 62 patients with UTUC and a solitary kidney evaluated long term outcomes after endoscopic kidney sparing surgery.
-Median follow up: 65 months
-73% never required dialysis
-Only 26% ultimately underwent RNU
-5 year cancer specific mortality: 20%
-Mean eGFR decline: 2.9 mL/min/1.73 m²/year
Recurrence was frequent, 70% at 5 years, highlighting that eKSS is not a one time treatment, but a long term disease management strategy requiring rigorous endoscopic surveillance.
👉 In carefully selected patients with an imperative indication, preserving the kidney can preserve much more than renal function.
Published in @BJUIjournal
Link: bjui-journals.onlinelibrary.…
#UTUC #Endourology #Ureteroscopy #KidneySparingSurgery #Urology
The study included 62 patients treated at two tertiary centres and found frequent recurrence but durable renal preservation with structured surveillance.
🤖 Made with AI

Meg Kulkarni 💙 retweeted
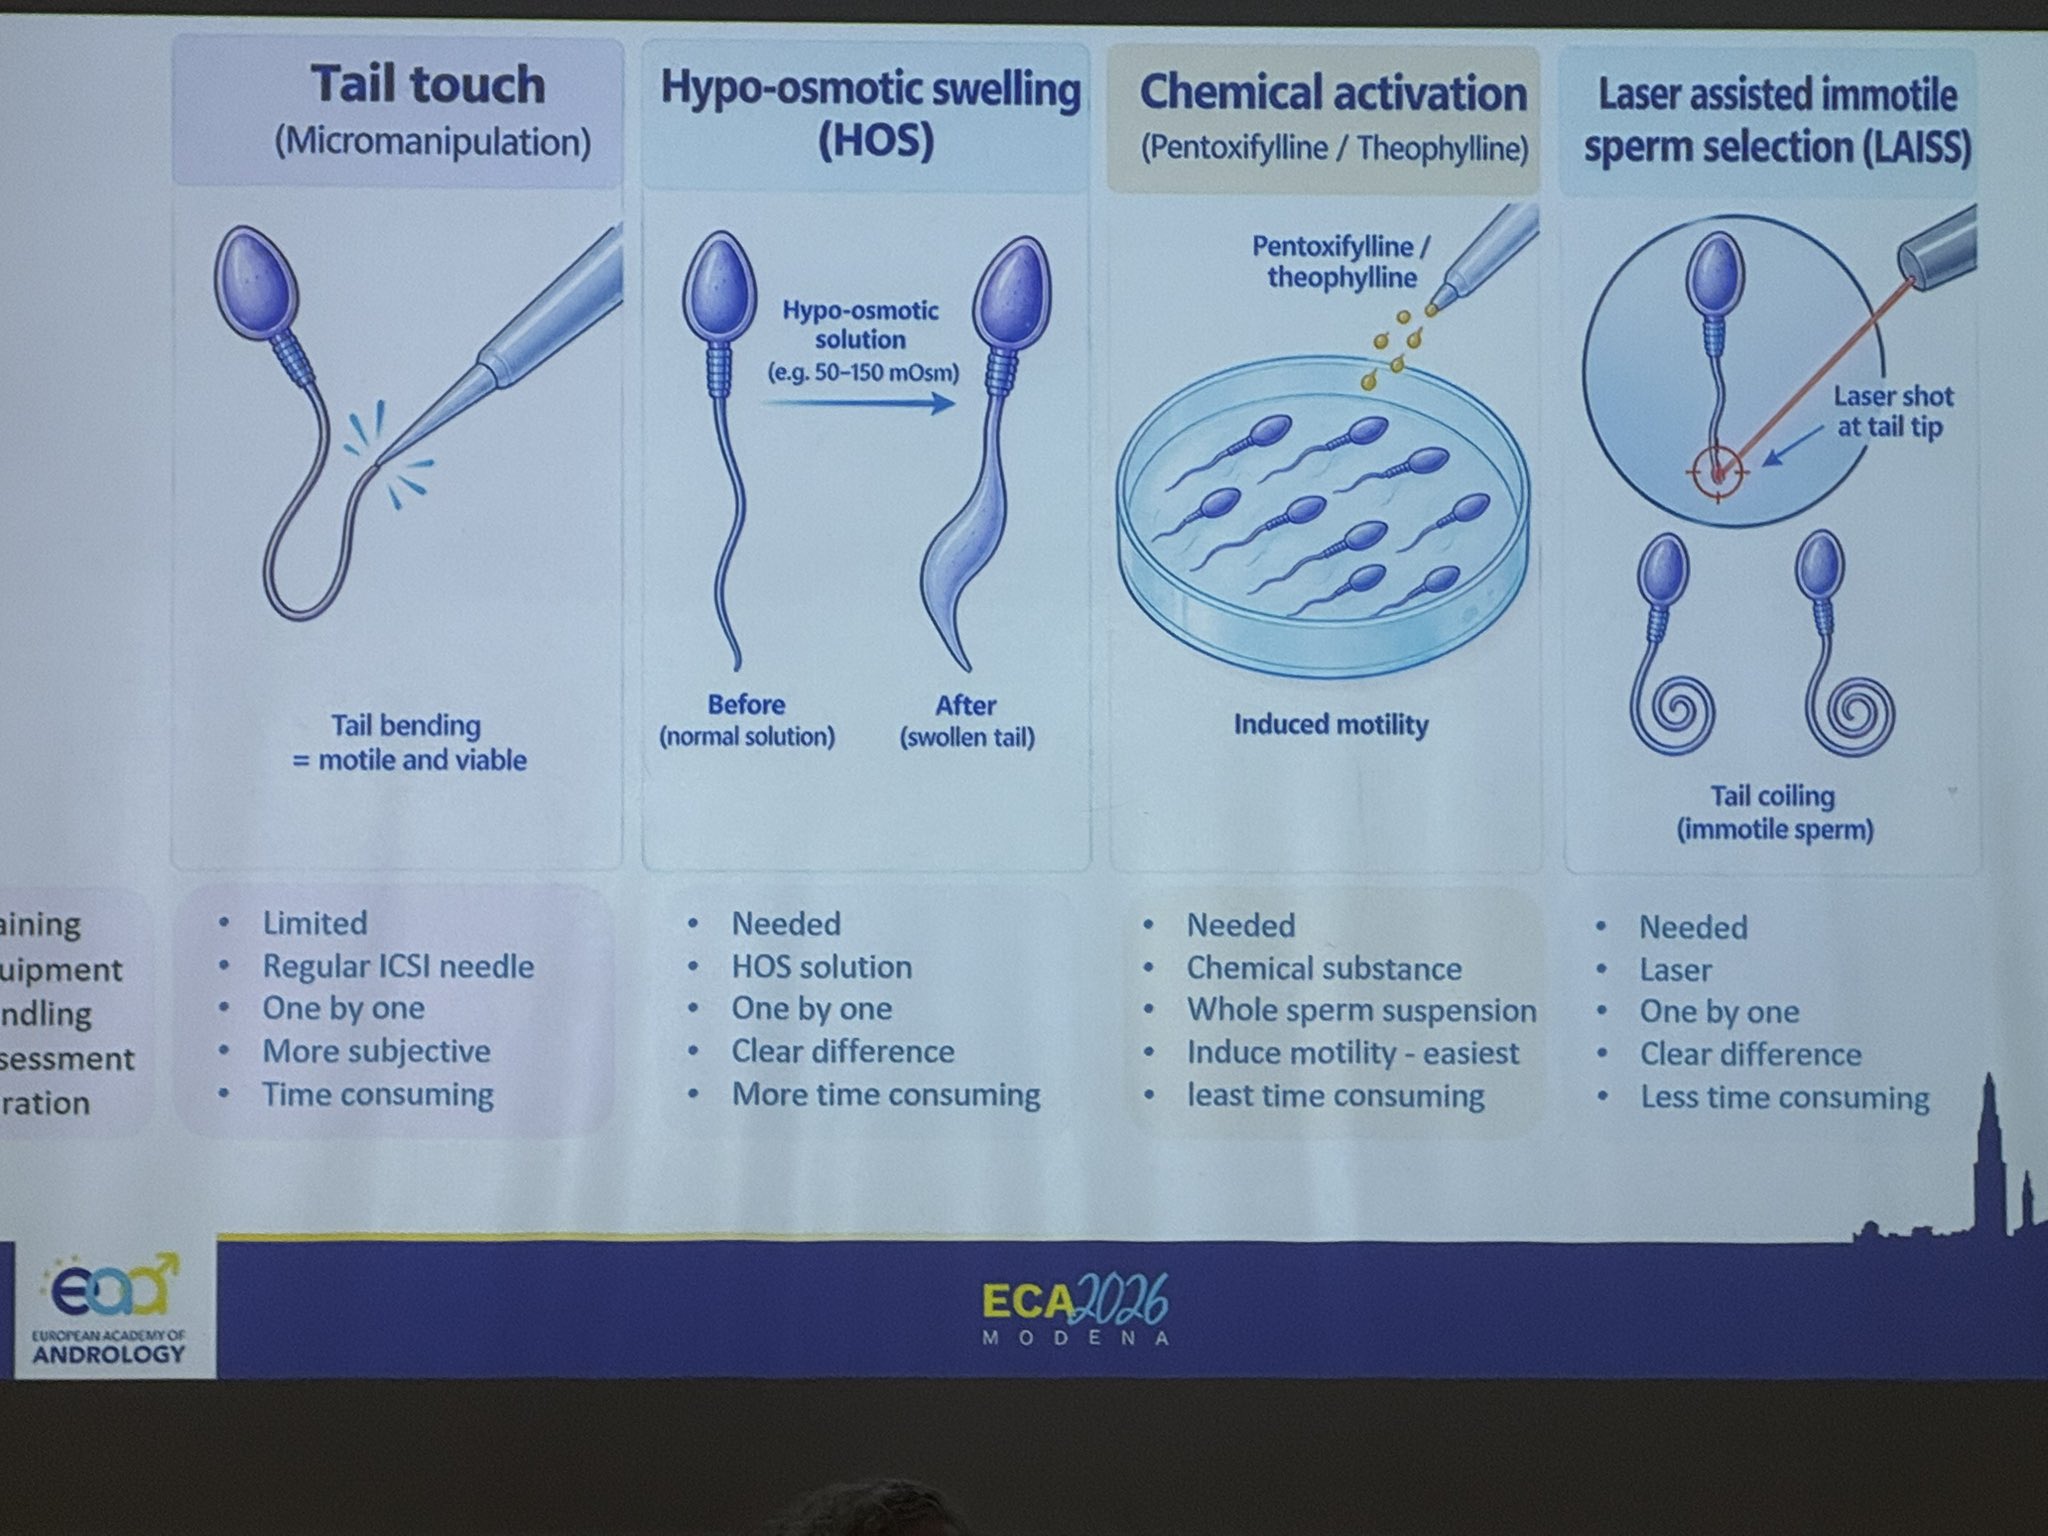
Excellent talk by Kaylee Holleman on Prmary Cilliary Dyskinesia and how our fantastic embryologists can assess sperm & ICSI outcomes @EAAndrology conference in Italy. Good to see not just endourology using “Lasers” … who knew they could be used to check sperm health


Meg Kulkarni 💙 retweeted
Another GP practice who instead of employing actual GP are instead employing non medical substitutes- here no mention anywhere of supervision - it’s like @lengreview never happened and the @NHS is simply carrying on - @rcgp very least you can write to these practices and ask why?

🚨New advert for a PA to work as a GP substitute @rcgp
‘ The PA will INDEPENDENTLY assess , diagnose and manage Pts with acute and chronic conditions‘
‘ provide first point of contact care for patients presenting with undifferentiated undiagnosed problems ‘


