




Mufaso retweeted

It’s her little shoes with perfectly tied laces by a mother who loved her that gets me. Now they’re both gone.

A horrific Russian strike in the Kharkiv region. A “shahed” struck people directly – in a park near an ordinary café. Pure atrocity. Six people were killed, including children. A little girl was killed in a stroller – her name was Angelina, she was just over a year old, born in August 2025… Her mother’s name was Inna. She died in the hospital… Another girl who was killed was 11 years old. My condolences to their families and loved ones. Another 14 people were injured, including six more children.
I am grateful to everyone who supports Ukraine under these circumstances and helps us shoot down “shaheds,” shoot down missiles, and stop Russian assaults. These are horrific photos, but behind them are shattered lives and the truth about this war. Lives must be protected. Ukraine needs air defense. You can't think about making money with Russia as long as it continues its asinine war. We ask that sanctions on Russia stay in place as long as the killings continue. We ask America to be strong, and we ask it to apply the Lindsey Graham law. We ask Europe to continue its support. We ask that everything possible be done to bring peace and guarantee security. Ukraine wants peace. It is Russia that has insisted on continuing the killing all this time. The world has enough strength to stop the war. That strength must finally be used – against the murderers.


No weekly arm in the SUNRISE phase 3. It’s three once-daily oral doses (27.5mg, 35mg, 55mg) plus placebo, 68 weeks.
In the Maintenance Part 2, also no weekly oral. Viking corrected the Oct 6 PR today- the weekly oral listing was an error. Part 2 is daily oral, every-other-week SC, monthly SC, or placebo after 21 weeks of weekly SC.
$VKTX - Oral VK2735 is positioned to be the first oral GLP-1/GIP dual agonist on the market‼️
The SUNRISE oral Phase 3 program targets only ~1,120 patients across two trials (560 each). That is roughly a quarter of the ~4,700 Lilly enrolled in ATTAIN-1 and ATTAIN-2 for orforglipron. 🤔
The smaller program is likely possible because oral VK2735 is the same molecule as SC VK2735, so it can lean on the VANQUISH safety database (~5,500 patients).
This should let oral VK2735 reach market at a fraction of the incremental R&D cost of new-molecule SMOL single agonists like orforglipron.

$VKTX ORAL VK2735 represents the most advanced oral dual GLP-1/GIP agonist in clinical development and has the potential to be positioned as either an induction therapy or in the maintenance setting, increasing the treatment options available to patients and clinicians
Wegovy pill (25mg QD) at 64 weeks got 16.6% WL% in OASIS 4 on an absolute basis (adherent estimand). Semaglutide seems to plateau around the ~60 week mark.
VK2735 Oral (60mg QD) in Venture ph2 at 13 weeks was 8.7%, again on an absolute basis. It is TBD to see where VK2735 will plateau.
➡️VK2735 55mg QD could surpass Wegovy 25mg QD if it simply plateaus at the same time and greatly surpass Wegovy 25mg if VK2735 has a later plateau for total WL% IMO. 🤔
As I’m certain you will reply to my message with “but the VK2735 API cost is prohibitive or something like that” let me simply say I strongly disagree. Yes, Novo Sema made in its hybrid recombinant/chemical process is likely the lowest cost means to create peptide API and specifically lower cost than VK2735.
That is not the whole story. Oral VK2735 could be made via TAPS, which is not far away cost wise, and if so the delta is not that great. Downstream processing (purification, tableting, absorption enhancer) and commercial costs (SG&A, channel) are separate arguments. Both drugs need this after initial API is made and on % basis reduce the overall Wegovy advantage significantly. NVO’s costs beyond API creation are likely much higher than VKTX especially if Viking goes the direct channel route which appears likely. And all these costs on a marginal basis reduce any API advantage Wegovy has.
Note that NOVO (like Lilly) has “golden handcuffs” and cannot simply reduce price forever to compete in obesity. Any low cost move they (or Lilly) makes in obesity will affect their T2D franchise. Viking with their cost structure will win any price war in Obesity with NOVO (or Lilly)‼️
Last- Viking could have made a marginal improvement in bioavailability for phase 3 without doing a bioequivalence study. They already tested some much higher doses with acceptable safety. Clearly Viking did some changes to their pill to reduce size so it is possible the changes reduced size, bioavailability (and cost).
Bottom line- VK2735 as the first dual oral GLP1/GIP agonist will be competitive with Wegovy oral IMO. (and LLY Foundayo or other SMOLs).
Mufaso retweeted

$PTGX UBS initiate
Buy $184 PT three potential drivers of outperformance over next 12mo 1) underappreciated commercial potential of PN-881 ("oral Bimzelx"), which view as $PTGX's most important pipeline value driver, 2) potential upward revisions to the Mimrylo royalty, where 2027/2028 estimates are 89% and 27% above consensus, 3) pipeline optionality from PN-477 (oral/injectable GGG) and PN-8047 (oral hepcidin), neither of which is reflected in our valuation and will have Phase 1 data in 2027.
$PTGX 881 is targeting 17Billion market with NEW ORAL MOA that’s currently dominated by injectables
To me, it sounds more like Neil was let go. If he left of his own accord, he would have a new position rather than be in a position where he was "... now taking some time to reflect before deciding on my next chapter"
Is BL up for a sale? I don't know but VK3019 is the wild card that needs to be turned over b4 a sale. No data in trials so far for VK3019 but that will change in less than 6 mos. I think BL is up for a sale above 10B+. JMHO
Mufaso retweeted

$VKTX
Not investment advice, just sharing 10+ years of my experience investing in the biotech sector.
Over that span, 22+ of my portfolio picks were eventually acquired. See my pinned tweet.
Why am I sharing this?
Many of those big wins, and some of you held these positions alongside me, including $STML $PRVB $DAWN $MYOV $JUNO $NARI $HZNP $RLYP $ITCI $KRTX, experienced irrational price action and significant pressure despite positive news, strong fundamentals, and continued clinical progress.
It was stressful watching a position trend lower while the underlying story remained intact.
But looking back, many of those extreme-fear-driven pullbacks turned into some of the biggest opportunities and, ultimately, substantial gains.
If you’ve spent enough time in biotech, you’ll see this pattern repeatedly, especially with clinical-stage companies.
The market can be extremely emotional in the short term. Fundamentals, clinical data, and execution often take time to play out.
You can sell into the fear and potentially regret it later, or, if your thesis remains intact, use those periods of irrational selling to reassess and potentially add.
Patience. Conviction. Execution.
That has been my approach for 10+ years in biotech.
Of course, there will be some losers down the road and that’s just part of the process. Move on and reassess what went wrong.
We can’t control the stock price, but to some extent, we can control our decisions.
Be well!
Depends on the comparison. I expect VANQUISH-1's population to look more like SURMOUNT-1's (BMI ~38) than TRIUMPH-1's (~40). My point is mainly that TRIUMPH-1's heavier population may goose reta's numbers a bit, so against reta, VK2735 could look slightly better than shown here.
Excellent post. 🙏 One caveat on the cross-trial comparison to reta TRIUMPH-1- its population was heavy: mean BMI 40.0 / 112.7kg at baseline vs 38.0 / 104.8kg in SURMOUNT-1. TRIUMPH-1 carried knee OA and OSA basket trials plus a BMI≥35 extension cohort, which likely pulled the average up. Just keep this in mind.
Great question! 🙏(You're reading it right and may be one of the few people to read the entire article😊)
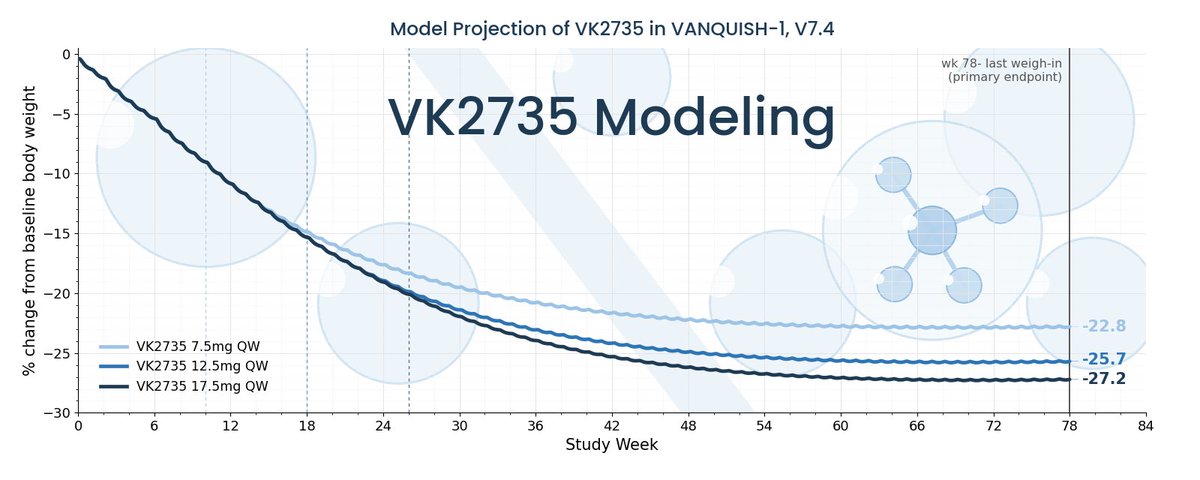
On the drug curve alone the model agrees with you- at wk 30 the VANQUISH-1 schedule sits about 1.8pp BEHIND the Maintenance schedule (-21.9% vs -23.7% on my chart's footing), because it reaches 17.5mg 14 weeks later. The two catch up by ~wk 48 and are the same line by wk 72.
➡️ What put the VANQUISH-1 line ahead of the Maintenance Trial's actual at wk 30 in my chart is the placebo term, not the titration. That chart carries SURMOUNT-1's placebo response (2.4pp) because VANQUISH-1, like SURMOUNT-1, counsels every arm on diet and exercise. The Maintenance Trial's placebo arm did nothing (-0.1 at wk 21, +0.3 at wk 33), so the two aren't on the same footing at wk 30. Strip the 2.4 out and VANQUISH-1 reads -19.6% at wk 30, under the Maintenance arm.
➡️ This is really the cross-trial issue from the article showing up inside my own chart- the drug curve is the same, the assumed placebo response of the trial around it is not.
I ran both titration schedules at 17.5mg (Maintenance and VANQUISH-1) through my model to illustrate the impact of the titration scheme on WL vs time- chart below, on the same footing as the article's projection.

$VKTX - I agree that vomit rate is a key indicator and I also watch that very closely.
➡I also care about when it happens. If it happens early and goes away I care a lot less about it (within reason).
➡This trial had an aggressive escalation and the PR said - "the incidence of GI-related adverse events was low and declined over time"
hmmm... Bodes very well for ph3 VANQUISH and lines up well with what you have been saying.
$VKTX - There was only 1 (as in ONE) discontinuation due to an AE in the induction phase of the Maintenance trial per the PR*. ONE, in an accelerated 2-week induction titration scheme‼ (I'm not talking about total DCs in induction, only the ones due to AEs.) For those of you good at math one out of ~161 treated in induction is less than 1%.
Discontinuations for other reasons (e.g., withdrew consent, lost to follow-up, protocol deviation) aren't reported, but the n's suggest they happened. There were 161 VK2735 subjects in the induction efficacy population and only 143 appear in the maintenance arms, so roughly 18 appear to have left during induction (I did the math).
➡I will repeat for clarity that only 1 (one) discontinued due to an adverse event out of 161 treated in induction. That is less than 1%. (@ChillBanking please feel free to comment😉)
➡This was in what many thought was a really aggressive titration scheme that would be problematic (not me, and certainly not Viking).
➡On GI AEs during induction, the PR says they were "characterized as mild" and that the incidence "was low and declined over time." Despite "the accelerated 2-week titration schedule," rates were "similar to those reported in the prior Phase 2 study" (VENTURE), "which utilized 3-week titration steps."
*Note: Here is the direct quote from the press release I refer to: "One subject (1%) in the induction period discontinued VK2735 treatment due to an adverse event."
Mufaso retweeted

$VKTX I don’t get the pile-on over this offering.
The deal launched at $400M and came out upsized to $500M, with Morgan Stanley and J.P. Morgan on the books. That is not a distressed dump. That is demand. Institutions do not throw hundreds of millions at a name they think is trash especially not the day after strong VK2735 maintenance data.
Retail sees dilution and hits sell. The people writing eight-figure tickets see cash for Phase 3, the oral program, and a shot at a slice of a huge obesity market. They have the model, the calls, and the allocation. The size of the book is the tell.
Strong demand on an upsized deal after good data is the story. Big money does not fund garbage at scale.
I would not be surprised with a big bear trap today.
Mufaso retweeted
$VKTX My July thread aged well — VK2735’s maintenance data reinforces how much cleaner its safety profile is versus retatrutide.

$VKTX Full thread on upcoming Maintenance Study results
Maintenance study is due this quarter, possibly in September. The significance of these results is substantial, and I will explain why in this thread.
Why this is an important readout: First, this trial will give us our first look at 31‑week weight‑loss data; until now, we’ve only seen results through 13 weeks.
Second, the subcutaneous dose is titrated up to 22.5 mg, offering insight into the impact of higher dosing. We’ll also get new information on switching from subcutaneous to oral, along with early signals on weekly oral dosing.
There’s a lot of data here, including the first look at monthly subcutaneous dosing. In total, we’ll be evaluating four distinct dosing regimens: weekly subcutaneous, monthly subcutaneous, daily oral, and weekly oral.
In summary, maintenance study results will also be important for topline data from the oral maintenance study, which will have read-throughs to the Ph3 program. Opportunity for VK2735 may be greater given it's a more potent dual GLP/GIP agonist and will also couple well with SQ VK2735 for seamless transition between SQ and oral formulations.
Advantage $VKTX as SQ VK2735 To Oral VK2735 offers a more seamless transition between Formulations. The fact that both the SQ and oral drugs are identical molecules formulated as oral and SQ. This should help mitigate some of the AEs associated with switching patients between different molecules.
Take a look at when patients were switched from SQ Wegovy or SQ tirzepatide to orforglipron, discontinuation rates went up. In the ATTAIN-MAINTAIN study by $LLY showed that when patients were switched from SQ semaglutide or SQ tirzepatide to orforglipron, D/C rates due to AEs were 4.8% and 7.2%, respectively. Also, patients who switched from Zepbound to orforglipron gained 11 lbs after 52 weeks on orforglipron.
Just a recap on $LLY Obesity portfolio
1) Retatrutide- Triple agonist, weekly subq injection. Efficacy- Weight at 80 weeks from avg. baseline: Retatrutide 4 mg -19.0%, 9mg -25.9%, 12mg -28.3%, Placebo 2.2%.
Safety- The most common adverse events among participants treated with retatrutide (4 mg, 9 mg, 12 mg, vs. placebo, respectively) were nausea (28.6%, 38.4% and 42.4% vs. 14.8%), diarrhea (25.2%, 34.1% and 32.0% vs. 13.5%), constipation (23.8%, 25.9% and 26.1% vs. 10.9%), vomiting (10.6%, 22.8% and 25.3% vs. 4.8%), and upper respiratory tract infection (14.2%, 12.2% and 13.1% vs. 11.6%). Incidences of dysesthesia occurred in 5.1%, 12.3%, and 12.5% of patients treated with retatrutide 4 mg, 9 mg, and 12 mg, respectively, compared with 0.9% with placebo.
2) Tirzepatide (Zepbound)- LLY's blockbuster drug is a dual GIP and GLP-1 receptor agonist like $VKTX 2735 which is currently in PH3 and reports data in 2027.
Efficacy- Average weight loss with tirzepatide of 26.6% from study entry over 84 weeks, 20.2% compared at 72 weeks
Safety- See the Chart below.
3) $LLY oral drug orforglipron, a small non-peptide for obesity
Efficacy- orforglipron showed placebo adjusted weight loss at 72 weeks of:
• -5.4% for 6 mg dosing
• -6.3% for 12 mg dosing
• -9.1% for 36 mg dosing- this is nothing earth shattering weight loss as it had been touted as the next blockbuster drug. In comparison, $VKTX VK2735 oral drug showed loss of 8.7% at 60mg dose in just 13 weeks. Weight loss of 12.2% at 120mg dose though higher D/C rates and side effects and not likely a viable dose from manufacturing standpoint.
Safety- Higher treatment D/C due to adverse events (10.3% at highest dose vs 2.6% placebo)
Significant gastrointestinal side effects reported (33.7% nausea, 25.4% constipation at highest dose)
Overall discontinuation rate of 24.4% at highest dose indicates tolerability challenges.
The most common adverse events for participants treated with orforglipron (6 mg, 12 mg and 36 mg, respectively) were nausea (28.9%, 35.9% and 33.7%) vs. 10.4% with placebo, constipation (21.7%, 29.8% and 25.4%) vs. 9.3% with placebo, diarrhea (21.0%, 22.8% and 23.1%) vs. 9.6% with placebo, vomiting (13.0%, 21.4% and 24.0%) vs. 3.5% with placebo, and dyspepsia (13.0%, 16.2% and 14.1%) vs. 5.0% with placebo. Treatment discontinuation rates due to adverse events were 5.1% (6 mg), 7.7% (12 mg) and 10.3% (36 mg) for orforglipron vs. 2.6% with placebo. The overall treatment discontinuation rates were 21.9% (6 mg), 22.5% (12 mg) and 24.4% (36 mg) for orforglipron vs. 29.9% with placebo.

Mufaso retweeted

The market still isn't pricing $VKTX correctly, but that's fine. This trial was a major de-risking event